
DEADLY POISONOUS
Paxillus syndrome is a rare immune reaction to Paxillus involutus that destroys red blood cells. Past meals without symptoms can be part of how it starts. Dark urine, shock, anemia and falling kidney function need emergency care.
Paxillus Syndrome: Hemolysis Risk From Brown Roll-Rim
Paxillus syndrome is a rare, potentially fatal reaction linked most clearly to the brown roll-rim, Paxillus involutus. You can eat this mushroom before without getting sick and still react badly to a later meal. That meal can bring vomiting, shock, clotting failure and acute kidney injury. Red blood cells can also burst inside the blood vessels, which doctors call intravascular hemolysis.
Warning signs that need emergency care
Call Poison Control at 1-800-222-1222 in the United States and seek emergency care when illness follows a suspected brown roll-rim meal. Call 911 for collapse, breathing trouble, confusion, seizure, severe weakness, chest pain, very dark urine, inability to wake the person, or signs of shock.
The first Paxillus symptoms look like the stomach upset many mushroom poisonings start with. Nausea, vomiting, belly pain and diarrhea may begin within hours. Then the illness can move past the gut as red blood cells break apart in the blood. Someone with what looked like a plain stomach bug can turn pale or yellow with jaundice, and feel breathless, weak, dizzy or confused.
Tell the emergency team about urine color. Red, tea-colored, cola-colored or very dark urine can come from blood, free hemoglobin, dehydration or muscle injury. Other causes need tests too. Less urine, or none, raises concern for kidney damage and poor blood flow. Dark urine is also the one sign here you can see with no equipment.
- Gastrointestinal opening
- Vomiting, diarrhea, and abdominal pain can appear early
- Hemolysis concern
- Pallor, jaundice, weakness, rapid pulse, and dark urine
- Shock concern
- Fainting, cold skin, confusion, low pressure, or breathing difficulty
- Kidney concern
- Falling urine output, flank discomfort, or worsening laboratory values
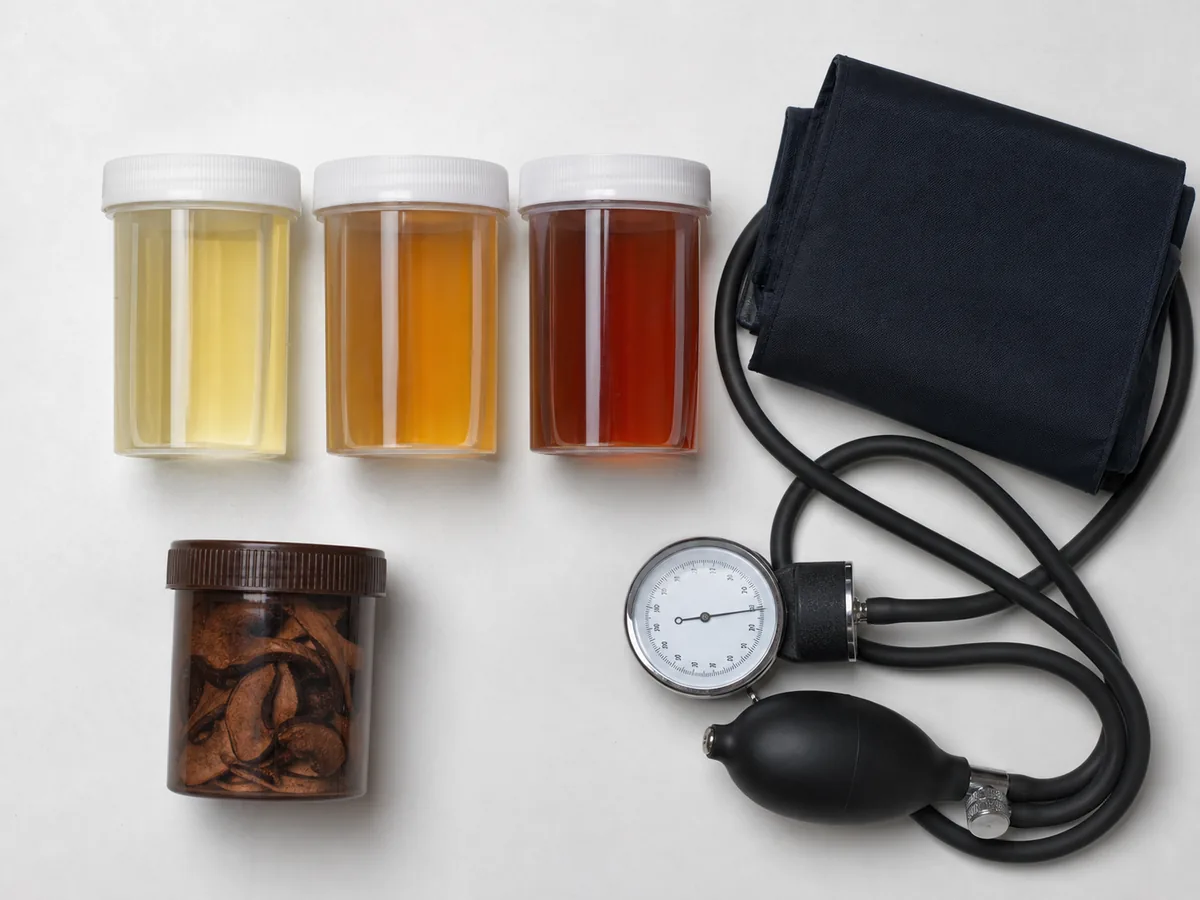
Do not induce vomiting or force fluids. Both home habits can backfire here. Repeated vomiting can pull vomit into the lungs, which doctors call aspiration. Shock, kidney damage or reduced alertness also change what the person can safely take.
Keep the leftover food from the meal. Write down the time of the first bite and the first symptom. Then follow the first-aid and transport advice from emergency and poison specialists. Each minute spent proving the mushroom's name at home delays the check on blood flow and hemolysis.
SafetyAmatoxin Poisoning: Organ Damage Timeline and CareWhat causes Paxillus syndrome?
Earlier meals of brown roll-rim do not prove it is safe for you. Those meals may be part of how the reaction builds. Published severe cases describe people who had eaten the mushroom again and again. Then a later meal set off a sudden immune attack on their red blood cells, called immune-mediated hemolysis.
- Prior exposure
- Earlier meals may prime an immune response without obvious illness
- Antibody evidence
- IgG reacting with Paxillus extract was demonstrated in a fatal case
- Proposed injury
- Immune complexes can attach to red-cell surfaces and activate complement
- Result
- Intravascular red-cell destruction can produce anemia, shock, and organ injury
The best-described cause is still an immune theory built from case reports. In a fatal 1982 report, a previously healthy 49-year-old man became gravely ill after eating the mushroom again and again. The authors found an IgG antibody that reacted with the mushroom extract. They proposed that immune complexes stuck to his red cells, switched on complement, and burst the cells inside his blood vessels.
One fatal case cannot tell you how often the syndrome happens. It does show that past meals without symptoms failed as a safety test. It also shows the chain of events can be deadly. Later reviews of its clinical toxicology still class it as immune-mediated hemolytic anemia tied to repeat meals.
So the immune history covers years, not just this week. Tell doctors if the person ate brown roll-rim as a child, as a seasonal food, after boiling or pickling, or on past trips. Rough dates, cooking methods and past symptoms can rebuild that past even with no medical record.
Diners at one table may not share the same immune past. One person can collapse while another stays well after the same dish. That gap does not clear the mushroom. Portion size, past meals, health and each person's immune response can all differ.
Most foods you have eaten many times without trouble keep agreeing with you. Brown roll-rim breaks that pattern. Like any poisonous mushroom, it does not become safe because someone ate it ten times before. No traditional recipe can make that immune response predictable or controlled.
Which mushrooms cause Paxillus syndrome?
Brown roll-rim, Paxillus involutus, is the species most clearly tied to the syndrome. Its cap is usually brown to olive-brown. On young caps, the edge stays tightly rolled under. The center often sinks with age, and the surface can feel velvety or turn sticky in wet weather.
| Feature | Useful observation | Identification limit |
|---|---|---|
| Cap margin | Thick and rolled inward on young specimens | Older caps flatten and lose the strongest roll |
| Gills | Crowded, forked, and running down the stem | Damage and cooking obscure attachment |
| Bruising | Gills and flesh may stain brown when handled | Brown staining occurs in other mushrooms |
| Spore deposit | Brown to ochre-brown | Spore color supports a genus-level hypothesis, not edibility |
| Habitat | Ground beneath birch, pine, and other trees | Tree association is shared by many mycorrhizal fungi |
Fresh gills give the best clues. They run down the stem, may fork and cross-link, and can often peel away from the cap flesh in one layer. Pressing them can leave brown stains. That clue tells you less once the mushroom is old, soaked or cooked.

Paxillus involutus forms mycorrhizal partnerships with trees. It fruits on soil near their roots, most often with birch and conifers across broad northern regions. You may find it by a path, a garden tree, heath or a woodland edge, and not only deep in a forest. The tree link adds to the collection story, but it cannot identify a cooked mushroom.

Common names add more doubt. Brown roll-rim, poison pax and brown pax may name the same species in other books. Other Paxillus species can look similar. Keep whole specimens, and use the scientific name only after a qualified expert has identified them. They back up the medical history, but gathering them should never delay treatment.
How red-cell destruction reaches the kidneys
Intravascular hemolysis means red blood cells burst inside the blood vessels. Normally the spleen clears red cells slowly. Fast bursting inside the vessels cuts how much oxygen the blood can carry. It also dumps hemoglobin straight into the plasma.
The blood then carries the damage to several organs. Losing red cells can cause pallor, weakness, breathlessness, a fast pulse and strain on the heart. Free hemoglobin can darken plasma and urine. The immune reaction and the burst cells can also stoke inflammation and unsteady blood flow.
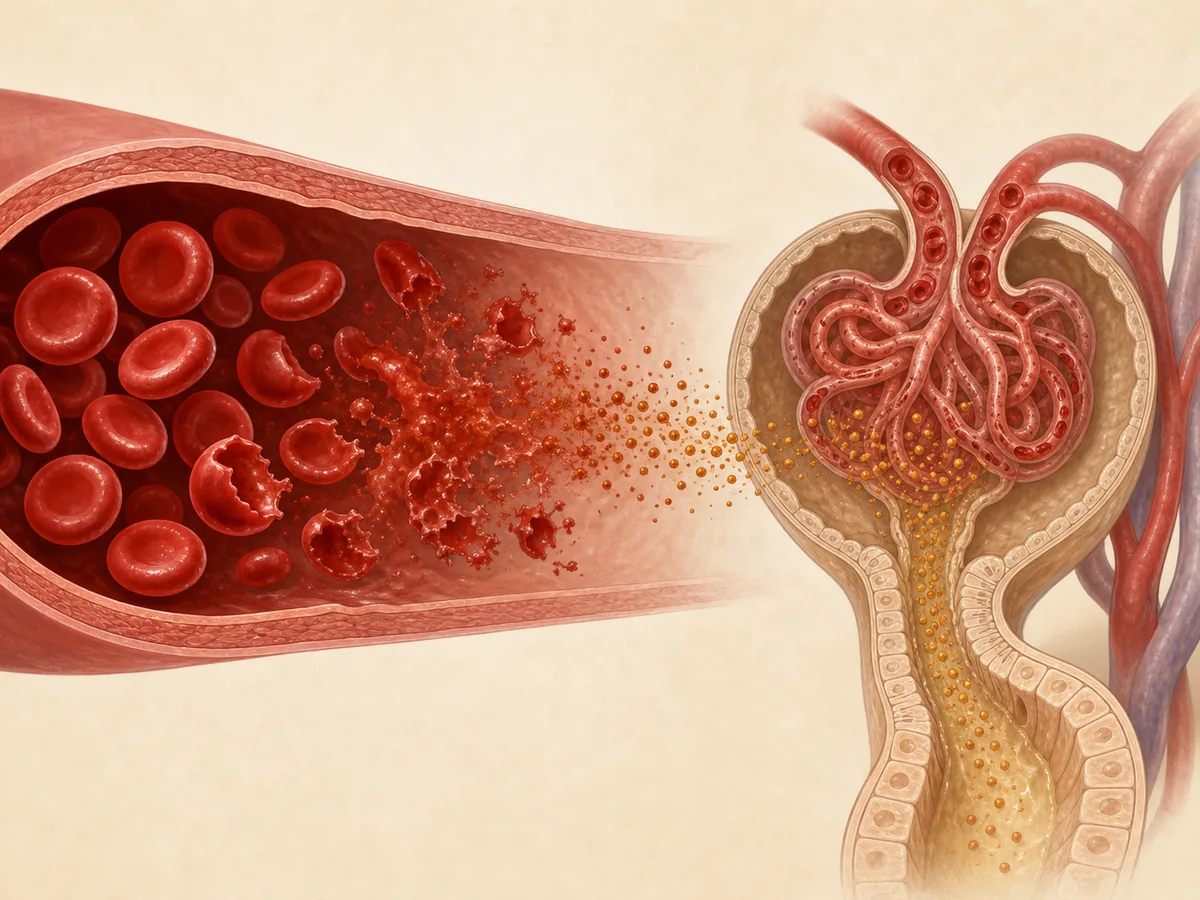
The kidneys face a double strain. Filtered hemoglobin can harm the kidney tubules, most of all if the person is short of fluids and the urine is acidic. Shock also cuts blood flow to the kidneys. Pigment damage and poor blood supply can then combine into acute kidney injury.
Clotting can fail in a severe whole-body reaction. The fatal case report described disseminated intravascular coagulation, plus acute kidney and respiratory failure. In that state, clotting switches on all over the body. It uses up platelets and clotting factors while small vessels and organs take damage.
Dark urine starts the medical questions and does not answer them. Doctors must find out whether it comes from hemoglobin, blood, muscle pigment or concentrated urine. They then track anemia, blood flow, clotting and kidney function together.
SafetyCoprine Mushroom Alcohol Reaction: Symptoms and When to ActPoisonings that can look like Paxillus syndrome
Vomiting soon after a wild mushroom meal does not point to one cause. Gut irritants, tainted food, allergy, amatoxin, kidney toxins and gyromitrin can all start the same way. So can some illnesses that have nothing to do with mushrooms.
Key takeaway
Paxillus syndrome enters the differential when the mushroom evidence and prior exposure fit, especially when hemolysis, shock, dark urine, or kidney injury appears. No single symptom proves the diagnosis.
Symptoms that start soon after the meal can point to an irritant, and they still do not rule out Paxillus poisoning. The brown roll-rim reaction itself may begin within hours. Mixed baskets can also add another toxin on a different timeline.
Stomach illness that starts late raises other concerns. Amatoxin poisoning can bring severe vomiting after a quiet gap. The person may then seem to improve before liver failure. Orellanine and other kidney toxins may delay kidney symptoms for days. They often lack the sudden hemolysis seen in Paxillus cases.
Allergy can bring hives, swelling, wheeze, throat tightness and low blood pressure. Anaphylaxis follows an emergency pathway even if the person ate a brown mushroom. Red-cell destruction alone needs a different lab workup. Infection or bad food is more likely when several diners share fever and stomach illness but no hemolysis. Mixed portions still muddy that comparison.
Dark urine after the meal also has many possible causes. Blood from the urinary tract can darken it. So can myoglobin after muscle injury, bilirubin from liver disease, dehydration, medicines and foods. Urine and blood tests show which pigment and organ problem is present. Until the trend and the evidence agree, the diagnosis stays a working guess.
Hospital care for shock, hemolysis and kidney injury
Emergency care starts with airway, breathing, blood flow and alertness. The team also checks temperature, oxygen, pulse and blood pressure. Doctors place an IV line, look for shock and ask about the meal. They also ask about earlier brown roll-rim meals, other diners, medicines and health problems.
Blood tests then follow the suspected injury. The complete blood count tracks falling hemoglobin. Bilirubin, lactate dehydrogenase, haptoglobin, reticulocytes and a blood smear describe the hemolysis. Electrolytes, creatinine, acid-base status, liver tests, glucose and clotting studies reveal organ damage. Urinalysis and urine output add to that picture and point to other diagnoses.
No single test confirms Paxillus, so doctors read the hemolysis pattern across several results. Red-cell destruction can raise indirect bilirubin and lactate dehydrogenase and use up haptoglobin. The bone marrow may answer with more reticulocytes. Blood draw timing, transfusion, liver function and how fast cells break down can shift that pattern, so doctors read trends next to the exam.
Immune tests add clues but cannot prove which mushroom caused the illness. The direct antiglobulin test shows if antibodies or complement sit on the red cells. Case reports describe special antibody tests, and these are not a routine quick check after field exposures. If nobody can run a Paxillus test, or it comes back negative, the species history and organ findings still stand.
Urine tests sort out why the urine is dark. The dipstick reacts to heme from intact red cells, free hemoglobin or myoglobin. Microscopy shows whether red cells are really there. Creatine kinase, plasma color and bilirubin add more clues. Hemolysis markers, kidney values and the exposure story then point to the pigment and injury at work.
Supportive care for hemolysis and kidney damage changes with the test results. Fluids and blood-pressure support must allow for shock and kidney function. Severe illness may need blood products, breathing support and intensive monitoring. Doctors also treat dangerous electrolyte or clotting problems.
No home antidote can replace that hospital support. Reviews of mushroom poisoning describe plasma exchange, hemodialysis, transfusion and other advanced steps in some severe cases. That evidence comes mostly from case reports and specialist practice. These treatments need a hospital decision, because timing, complications and risks differ between patients.
Dialysis supports kidney and metabolic work when the damage turns severe. It does not undo the immune event or promise recovery, so doctors keep tracking hemolysis and other organs. Kidney, blood, poison and critical care specialists may each handle part of the case, along with a mycologist.
The mushroom's name never comes before stabilizing the patient. The photos can go to an expert later. Shock, breathing failure, high potassium (hyperkalemia), severe anemia or clotting failure needs treatment as soon as doctors spot it.
SafetyGastrointestinal Mushroom Poisoning: Timing and CareEvidence to save from the meal
Save whole raw specimens with the cap, gills, stem and base intact. Keep cooked leftovers, cleaning scraps, photos, containers and notes apart from any food someone might eat. If a mature cap remains, a spore print can keep useful color, but it should never delay emergency care. Photograph the print, cap surface, underside, bruising and habitat in neutral light, and leave the colors unedited.
Write the current meal as a timeline. Record the first bite, portion, preparation and first symptom. Add urine changes, fainting, treatment and every change during transport. Give each diner's portion and symptoms their own line, because group averages hide each person's exposure.
For Paxillus, the person's lifetime mushroom history belongs in the record too. Ask about brown roll-rim, poison pax, brown pax, mushrooms picked under birch or pine, and preserved meals from earlier years. The person may remember the dish by a local name or a recipe, and not by the scientific name.
Cooking and preserving details round out the history and the ID. Note boiling, discarded water, pickling, drying, frying, freezing and any change in looks. None of these steps reliably removes the risk of an immune-mediated syndrome. If the meal used preserved mushrooms, save the jars, labels, freezer bags and dates.
Someone who ate the same meal and stayed well is a useful but limited clue. That person may have eaten fewer mushrooms or a different cap. They may also lack the same past exposure and immune response. Report the difference, but never use it to reassure the person who is ill. The evidence should travel with the patient and never hold up care.
Recovery across several organs
Vomiting can stop before hemolysis, anemia or kidney damage has settled. Feeling better starts a watch period and does not prove the crisis is over. Doctors watch which way repeated blood and kidney results move. Hemoglobin, hemolysis markers, blood pressure, pulse, oxygen needs, urine output, creatinine, potassium, acid-base status, platelets and clotting tests can each improve on their own schedule. One better result means little without the values before and after it.

Kidney recovery may lag behind blood flow and hemolysis. Some patients with severe kidney damage need dialysis for a while, until urine output and filtering recover. Others can keep lasting damage. Anemia, tiredness and low stamina may follow yet another timeline. They can linger even after the immune attack has stopped.
- Circulation
- Stable pressure and pulse without escalating support
- Hemolysis
- Hemoglobin and destruction markers move in the right direction
- Kidney function
- Urine output, creatinine, potassium, and acid-base balance stabilize
- Whole-person recovery
- Breathing, alertness, walking, intake, and follow-up are safe
Discharge plans after kidney injury and anemia include advice on when to come back, plus repeat tests if doctors want them. New dark urine, less urine, fainting, breathlessness, jaundice, bleeding, fever, severe weakness or repeated vomiting needs a prompt recheck. Organ problems can change after the first improvement.
Can brown roll-rim ever be safe to eat?
Treat brown roll-rim as poisonous and leave it out of every meal. Old local use, family habit, boiling, pickling and earlier meals without symptoms cannot control the immune risk seen in severe cases.
Nobody can put a number on your own risk, because rare case reports cannot show how likely a reaction is. Still, a syndrome that can cause hemolysis, shock, kidney failure and death leaves no safe home test. Eating a small portion to check tolerance just repeats the exposure and answers nothing.
Keep brown roll-rim out of mixed baskets. Do not carry it in the same container as edible mushrooms, because broken gills and cap bits can become impossible to sort later. Wash the container and tools before they go back to food use.
Teach other pickers the brown roll-rim paradox directly. Tell them a past meal without symptoms is part of the warning history and does not prove a later meal will be safe. Use the scientific name Paxillus involutus next to local common names so the warning survives travel and translation. The safest future exposure is none.
Sources3
- Deutsche Medizinische Wochenschrift 1982: fatal immunohaemolytic anaemia after eating Paxillus involutus, PubMed abstract 1982 fatal case after repeated meals; IgG antibody against the mushroom extract; immune-complex hemolysis
- Clinical Toxicology of Mushroom Poisoning (Dtsch Arztebl Int 2020) Paxillus poisoning as IgG-mediated hemolysis after repeated meals; hemodialysis, plasmapheresis and blood products as options
- Mushroom poisoning: an updated review, Turkish Journal of Emergency Medicine 2025 Amatoxin quiet interval: symptoms improve while liver injury develops
Frequently Asked Questions
What is Paxillus syndrome?
It is a rare reaction to brown roll-rim, Paxillus involutus, and it can be fatal. The immune system can burst red blood cells inside the vessels, which doctors call intravascular hemolysis. Shock, clotting problems and acute kidney injury can follow.
Can brown roll-rim become safe after boiling?
No way of preparing it, boiling included, makes the immune risk predictable. Old local use and past meals without symptoms do not prove it is safe either.
Why do previous meals matter?
Severe cases have followed many earlier meals of brown roll-rim. Case reports point to an antibody reaction, so those earlier meals may be how the body became primed.
Which symptoms need emergency care?
Collapse, breathing trouble, confusion, severe weakness or jaundice after a suspected meal needs emergency care right away. So do very dark urine, less urine, fainting and shock.
Does dark urine prove Paxillus syndrome?
No. Blood, hemoglobin and muscle pigment can all change urine color. So can bilirubin, dehydration, medicines and foods. Only lab tests can show which cause is present.